
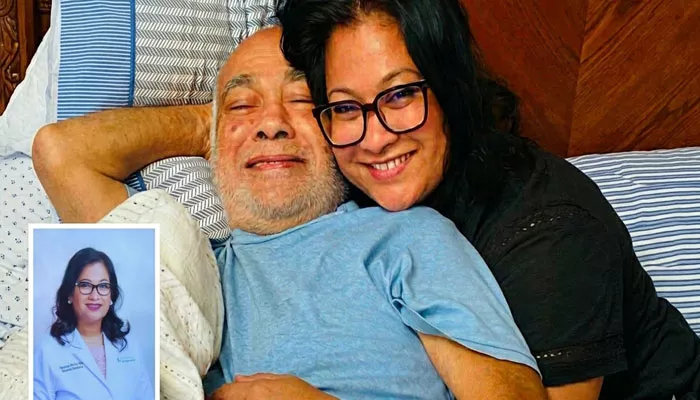
Dr. Samina Azam
What I am writing is not intended to blame or attack any particular doctor, nurse, or hospital. As a physician, I know how difficult and mentally exhausting critical care medicine can be. I know that countless healthcare workers work tirelessly every day under extreme pressure to save lives.
But I’m sharing my father’s story because silence will not protect future patients. I’m sharing it because I believe that right now, we need more awareness, accountability, stronger infection control systems, and a healthcare culture where patient safety is seen as a sacred duty. If reading this makes even one family more aware, one healthcare worker more vigilant, or one hospital strengthen their infection prevention measures — then my father’s suffering will not be entirely in vain.
My father survived a lot in life — but in the end, he succumbed to the very hospital system that was supposed to heal him. And that makes me wonder: How many more loved ones do we have to lose before we start to prioritize hospital-acquired infections and delayed emergency care?
Even at the age of 83, despite multiple chronic illnesses, Abba was very disciplined about his health. He was physically active, mentally alert, and took great pride in his good health reports. He would often call me and happily tell me that he had once again “passed with flying colours” in all his exams.
As he got older, he developed mild dementia, but it was kept fairly under control with medication, a regular routine, and mental exercise.
Then came August 5, 2024 — a terrible turning point in our lives. At the age of 82, he was arrested on a false charge and spent nearly 10 months in prison. During that time, he did not receive proper treatment and regular medication, resulting in his dementia rapidly deteriorating. Prolonged loneliness irreparably damaged his mental capacity. Those who have cared for a dementia patient know — how important family, familiar surroundings, conversation, and emotional connection are. Gradually, solitary confinement begins to take that person away from us.
At one point, he almost died of sepsis and had to undergo ICU treatment at PG Hospital and later at Square Hospital. By the grace of God, he survived the service. After being released on bail and returning home, he was so weak that he needed the help of two people to go to the bathroom. But with strong morale, physical therapy and an indomitable will, he gradually regained some normalcy. Within a few months, he started walking on his own with a walker. His short-term memory was poor, but he could still recognize loved ones, tell stories from the past and participate in conversations.
Advertisement
Then another tragedy struck our family.
Last March, my uncle collapsed and was admitted to the hospital. Shortly after he was discharged, he developed severe shortness of breath and had to be readmitted. He was diagnosed with hospital-acquired pneumonia caused by a very dangerous and often multi-drug resistant bacteria called Acinetobacter. He was intubated and taken to the ICU, where he eventually died. My father visited him and attended his funeral in the village.
About ten days after returning home, Abba developed fever and shortness of breath. He was admitted to the hospital and diagnosed with Haemophilus influenzae pneumonia. Due to his interstitial lung disease, he had to be given high-flow oxygen and was admitted to the HDU. At that time, a Foley catheter was inserted into his body, which was left in place for about ten days.
When his breathing improved a bit and his oxygen requirement decreased, he was transferred to a cabin. That’s when I arrived to see him. I was very concerned about the risk of infection due to the Foley catheter being in place for so long. I repeatedly requested it to be removed and finally it was removed. Alhamdulillah, he recovered enough to be discharged home.
For three beautiful days, he seemed to be getting better again. He started physical therapy again and would walk from his bedroom to the living room to eat with us. Today, those simple moments seem priceless.
Then suddenly on the third day he developed a high fever, chills and rigors. His condition rapidly deteriorated and urinary retention developed. We rushed him to the emergency department, where a Foley catheter was reinserted and urine tests were sent. He was sent home again, but throughout the day I could tell he was becoming septic. We rushed him back to the hospital.
What happened next was one of the most difficult experiences of my life.
Even after being admitted to the hospital, it took several hours to collect his blood tests and cultures. I kept saying that he was becoming septic and needed antibiotics urgently, but I was told that they were waiting for the consultant to arrive. As soon as the consultant arrived, the seriousness of his condition was understood and treatment began.
Then came more heartbreaking news. During his previous admission, his sputum culture had been positive for hospital-acquired Acinetobacter — the same dangerous bacteria found in my uncle’s body — and coagulase-negative staph. Yet none of us had told him about it after he was discharged from the hospital. As a result, he was taking antibiotics at home that were ineffective against the infection.
A few days later, his urine and blood cultures were positive for CRE Klebsiella — another highly resistant hospital-acquired organism, which I strongly believe was associated with prolonged Foley catheter use.
His body could no longer take the terrible strain of the infection.
His atrial fibrillation began and his heartbeat remained fast for a long time, eventually leading to heart failure. Again, there was a delay in emergency treatment. Before a specialist could be involved, his breathing became increasingly difficult due to pulmonary edema.
I watched my father struggle for every breath as water accumulated in his lungs. I repeatedly requested rapid diuresis and emergency intervention, but the delays continued. Eventually he developed flash pulmonary edema and had to be transferred to the ICU for high-flow oxygen support. He was then put on BiPAP before aggressive treatment could be initiated. Gradually, he stabilized somewhat and was moved down to nasal cannula oxygen. For a while, we were hopeful.
But that cycle didn’t stop.
Just before I returned to the US, I noticed that he was becoming lethargic again and needed more oxygen. His blood gas report showed carbon dioxide retention. I requested that BiPAP be restarted, but was again told to continue monitoring.
I returned to the US with deep anxiety and fear.
Soon after arriving in the US, terrible news began to come from my family. His breathing became worse. His blood pressure dropped. He had to be put on vasopressors. Unfortunately, he relapsed for the second time in the ICU and his CRP rose from 74 to 238. Again, the blood culture showed a large bacterial growth, although it was still not fully detected. His kidneys began to fail. Despite the risk of further kidney damage, aggressive diuresis was continued until his kidneys completely stopped working. Then a nephrology consultation was performed and dialysis was started.
By then, my father was almost in a coma. He would open his eyes occasionally, but his body had taken too much. He endured dialysis all night, but in the morning he no longer had the strength to fight.
And then we lost him forever.
One thing that deeply moved me during those 15 days in the ICU. Initially, he was kept in isolation due to a multidrug-resistant infection and family members were also restricted from entering. But I repeatedly saw health workers moving from room to room without proper gowns, gloves or masks. That’s when I understood why these infections spread so quickly.
Our family wore full PPE every time they entered his room after receiving permission, but many healthcare workers did not do so routinely. How can hospital-acquired infections be controlled if infection control protocols are not strictly followed? At one point, we were even told that parts of the oxygen system might have been contaminated. It all became a never-ending and terrifying cycle.
As a physician trained in the United States, I was deeply troubled by the shortcomings I witnessed — delays in recognizing emergencies, delays in initiating treatment, weak infection control measures, lack of proper communication of important culture results, and a system that was often activated only after a patient’s condition had deteriorated significantly.
And this leaves me with an even more painful question:
If I have to struggle so much to effectively fight for my father, despite being a doctor myself, what about ordinary families — who don’t even know the warning signs of sepsis, respiratory failure, or multidrug-resistant infection?
Families bring their loved ones to the hospital with faith and hope. They think the ICU is the safest place. But from what I have seen, it seems that in many cases, vulnerable patients are trapped in a vicious cycle of invasive devices, hospital-acquired infections, delayed interventions, and preventable complications.
My father fought his whole life — for his country, for his family, for his health. Even in the midst of dementia and serious illness, he fought to the end. But eventually his body could no longer withstand the relentless pressure of resistant infections and repeated complications.
Today I am not just writing as a grieving daughter. I am writing as a doctor, as a human being, and as a person hoping for change.
How do we stop this cycle?
How do we better protect at-risk ICU patients from hospital-acquired infections?
How do we ensure rapid identification of signs of sepsis and severe deterioration?
How do we strengthen the immune system to prevent the spread of multidrug-resistant bacteria from patient to patient?
How do we build a health system where families feel informed, heard, and safe?
And most importantly — how many more families must watch their loved ones slowly disappear before meaningful reforms in patient safety and infection control are considered national priorities?
Finally, I would also like to acknowledge that the consultants consistently understood the seriousness of my father’s condition and sincerely tried to provide the highest level of medical care. Despite their dedication, experience and compassion, they were ultimately unable to save my father due to the additional patient load and overall system constraints.

https://stapravda.ru/20221228/reyting_samyh_populyarnyh_hostingov_v_rossii_196445.html, рейтинг хостингов России подтверждает, что выбор надежного провайдера важен для бизнеса.